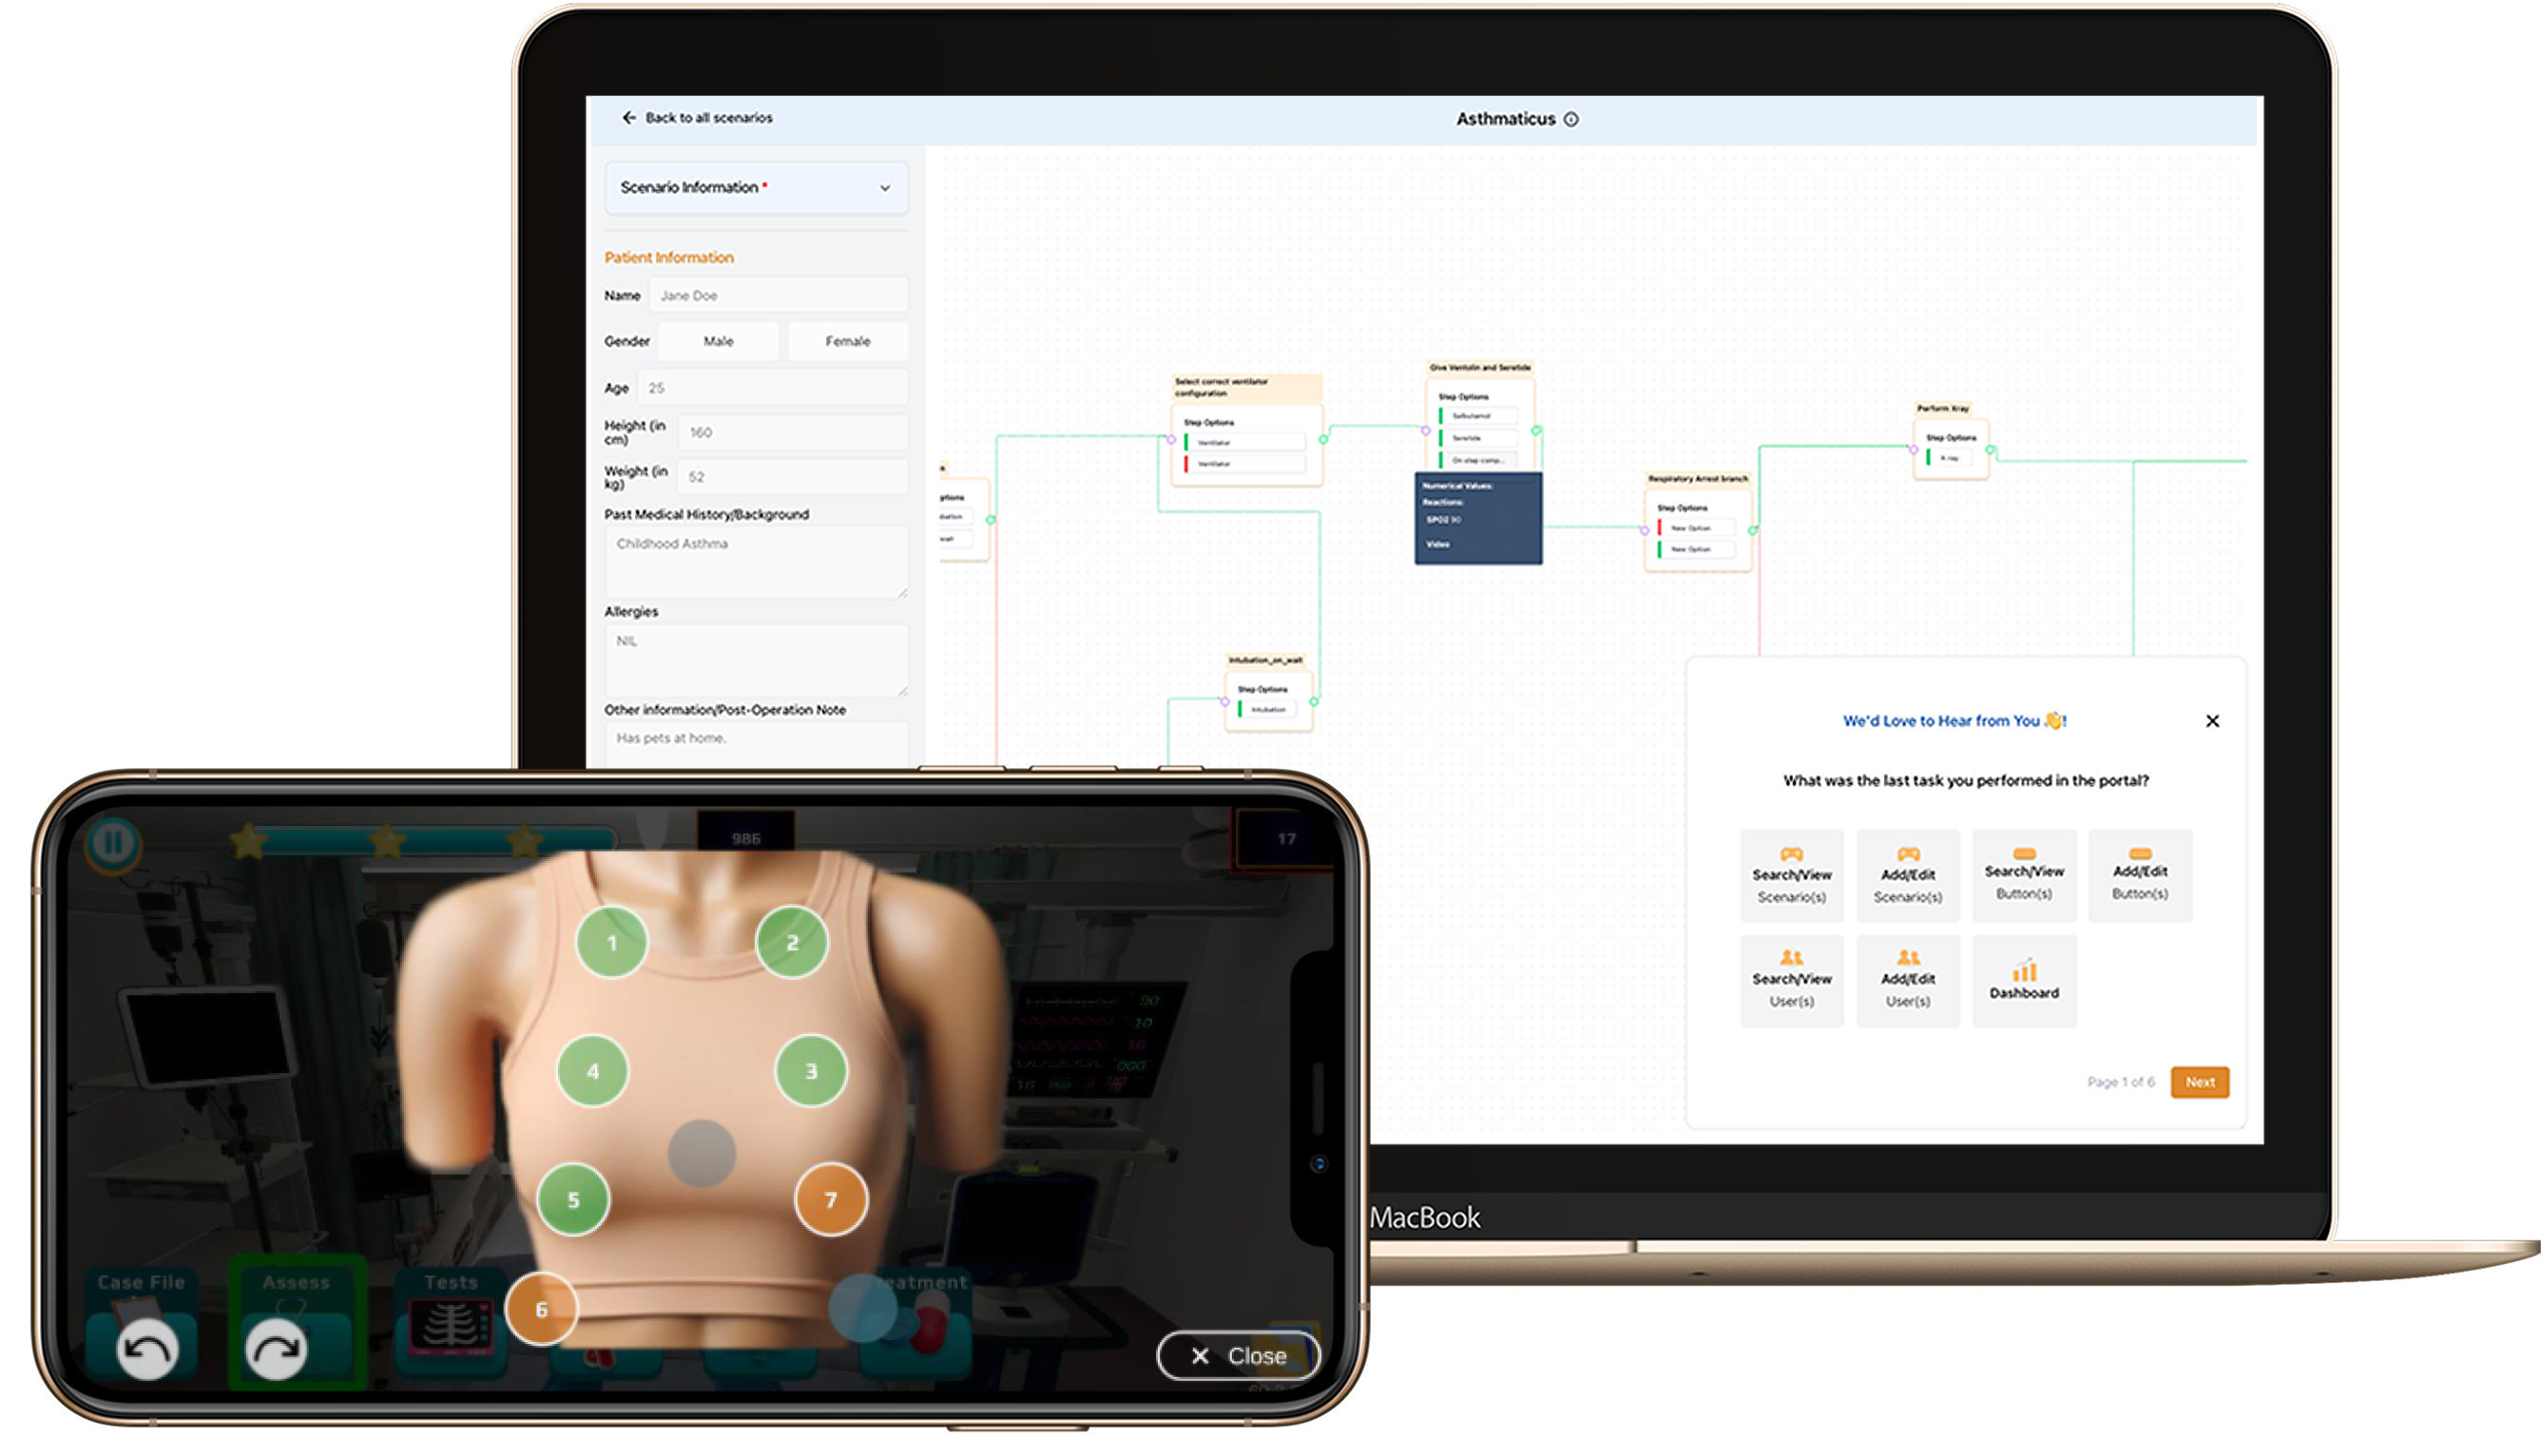
01 / Preparing for the demand
Hiring nurses was never going to be enough on its own.
The attrition rate among nurses has been rising for five years, pushing the nurse-to-patient ratio from 1:3.75 to 1:10. That pushed the government to hire 4,000 nurses in 2023 — but hiring is only part of the solution. Once hired, they still need to be trained, to keep patient care quality intact.
All health professionals, including nurses, don't hit the ground running, and need an appropriate period of supervision and mentoring, the specifics of which would depend on training and prior experience.
Dr Jeremy Lim, public health specialist
This project marked my first foray into game development, and the challenge that came with it: since the end users would be instructors, not developers, the solution had to require zero coding skill to operate.
02 / User needs discovery
Getting first-hand experience of the induction program.
To truly understand the end-user's perspective, we immersed ourselves in the ICU department to experience its atmosphere firsthand — starting at the learning centre, then observing live ICU rooms.
Cognitive overload, both when undergoing training and when handling a live patient case. Beyond operating machinery, nurses had to monitor conditions and make critical decisions at the same time — they had to learn to prioritise and act decisively.
Lack of practice, caused by limited access and availability. Permissions are required to use essential machines, so junior nurses' opportunities to learn are often opportunistic, not guaranteed.
Disorganised information, taught informally and on a feel basis. Critical information — treatment protocols, expected physiological responses — is scattered across preceptors, with little standardisation.
Together, these insights pointed to a solution that had to be both engaging and accessible — but without a clear, well-organised structure, information would just become another barrier instead of removing one.
03 / Setting the direction
Bite-sized, scalable, and visually honest.
Further interviews with nurses surfaced three requirements: bite-sized information that doesn't overload; scalability, so new scenarios can be added and disseminated as training needs evolve; and visual reinforcement, so nurses can see the real impact of their decisions on a patient.
An accessible, bite-sized format that lets nurses practice decisions and see their impact.
The solution also had to let administrators seamlessly add new scenarios themselves, to keep pace with evolving training needs — a requirement that would end up shaping almost every decision from here on.
04 / The real complexity
From a linear template to one that branches and loops.
Once the format was set, my team went deeper into the content itself. There was no existing resource or structure for it, so we gave nurses a template and a sample scenario to work from.
We quickly realised the scenarios were far more complex than we'd anticipated. Clarifying them took extensive back-and-forth — every detail had to be understood as accurately as possible, and every feature we proposed had to stay scalable.

Coverage
How could we be sure we had every necessary medication? Could the client even provide a comprehensive list?
Time
Gathering every piece of medication information was time-consuming — and it was never obvious why something had been missed.
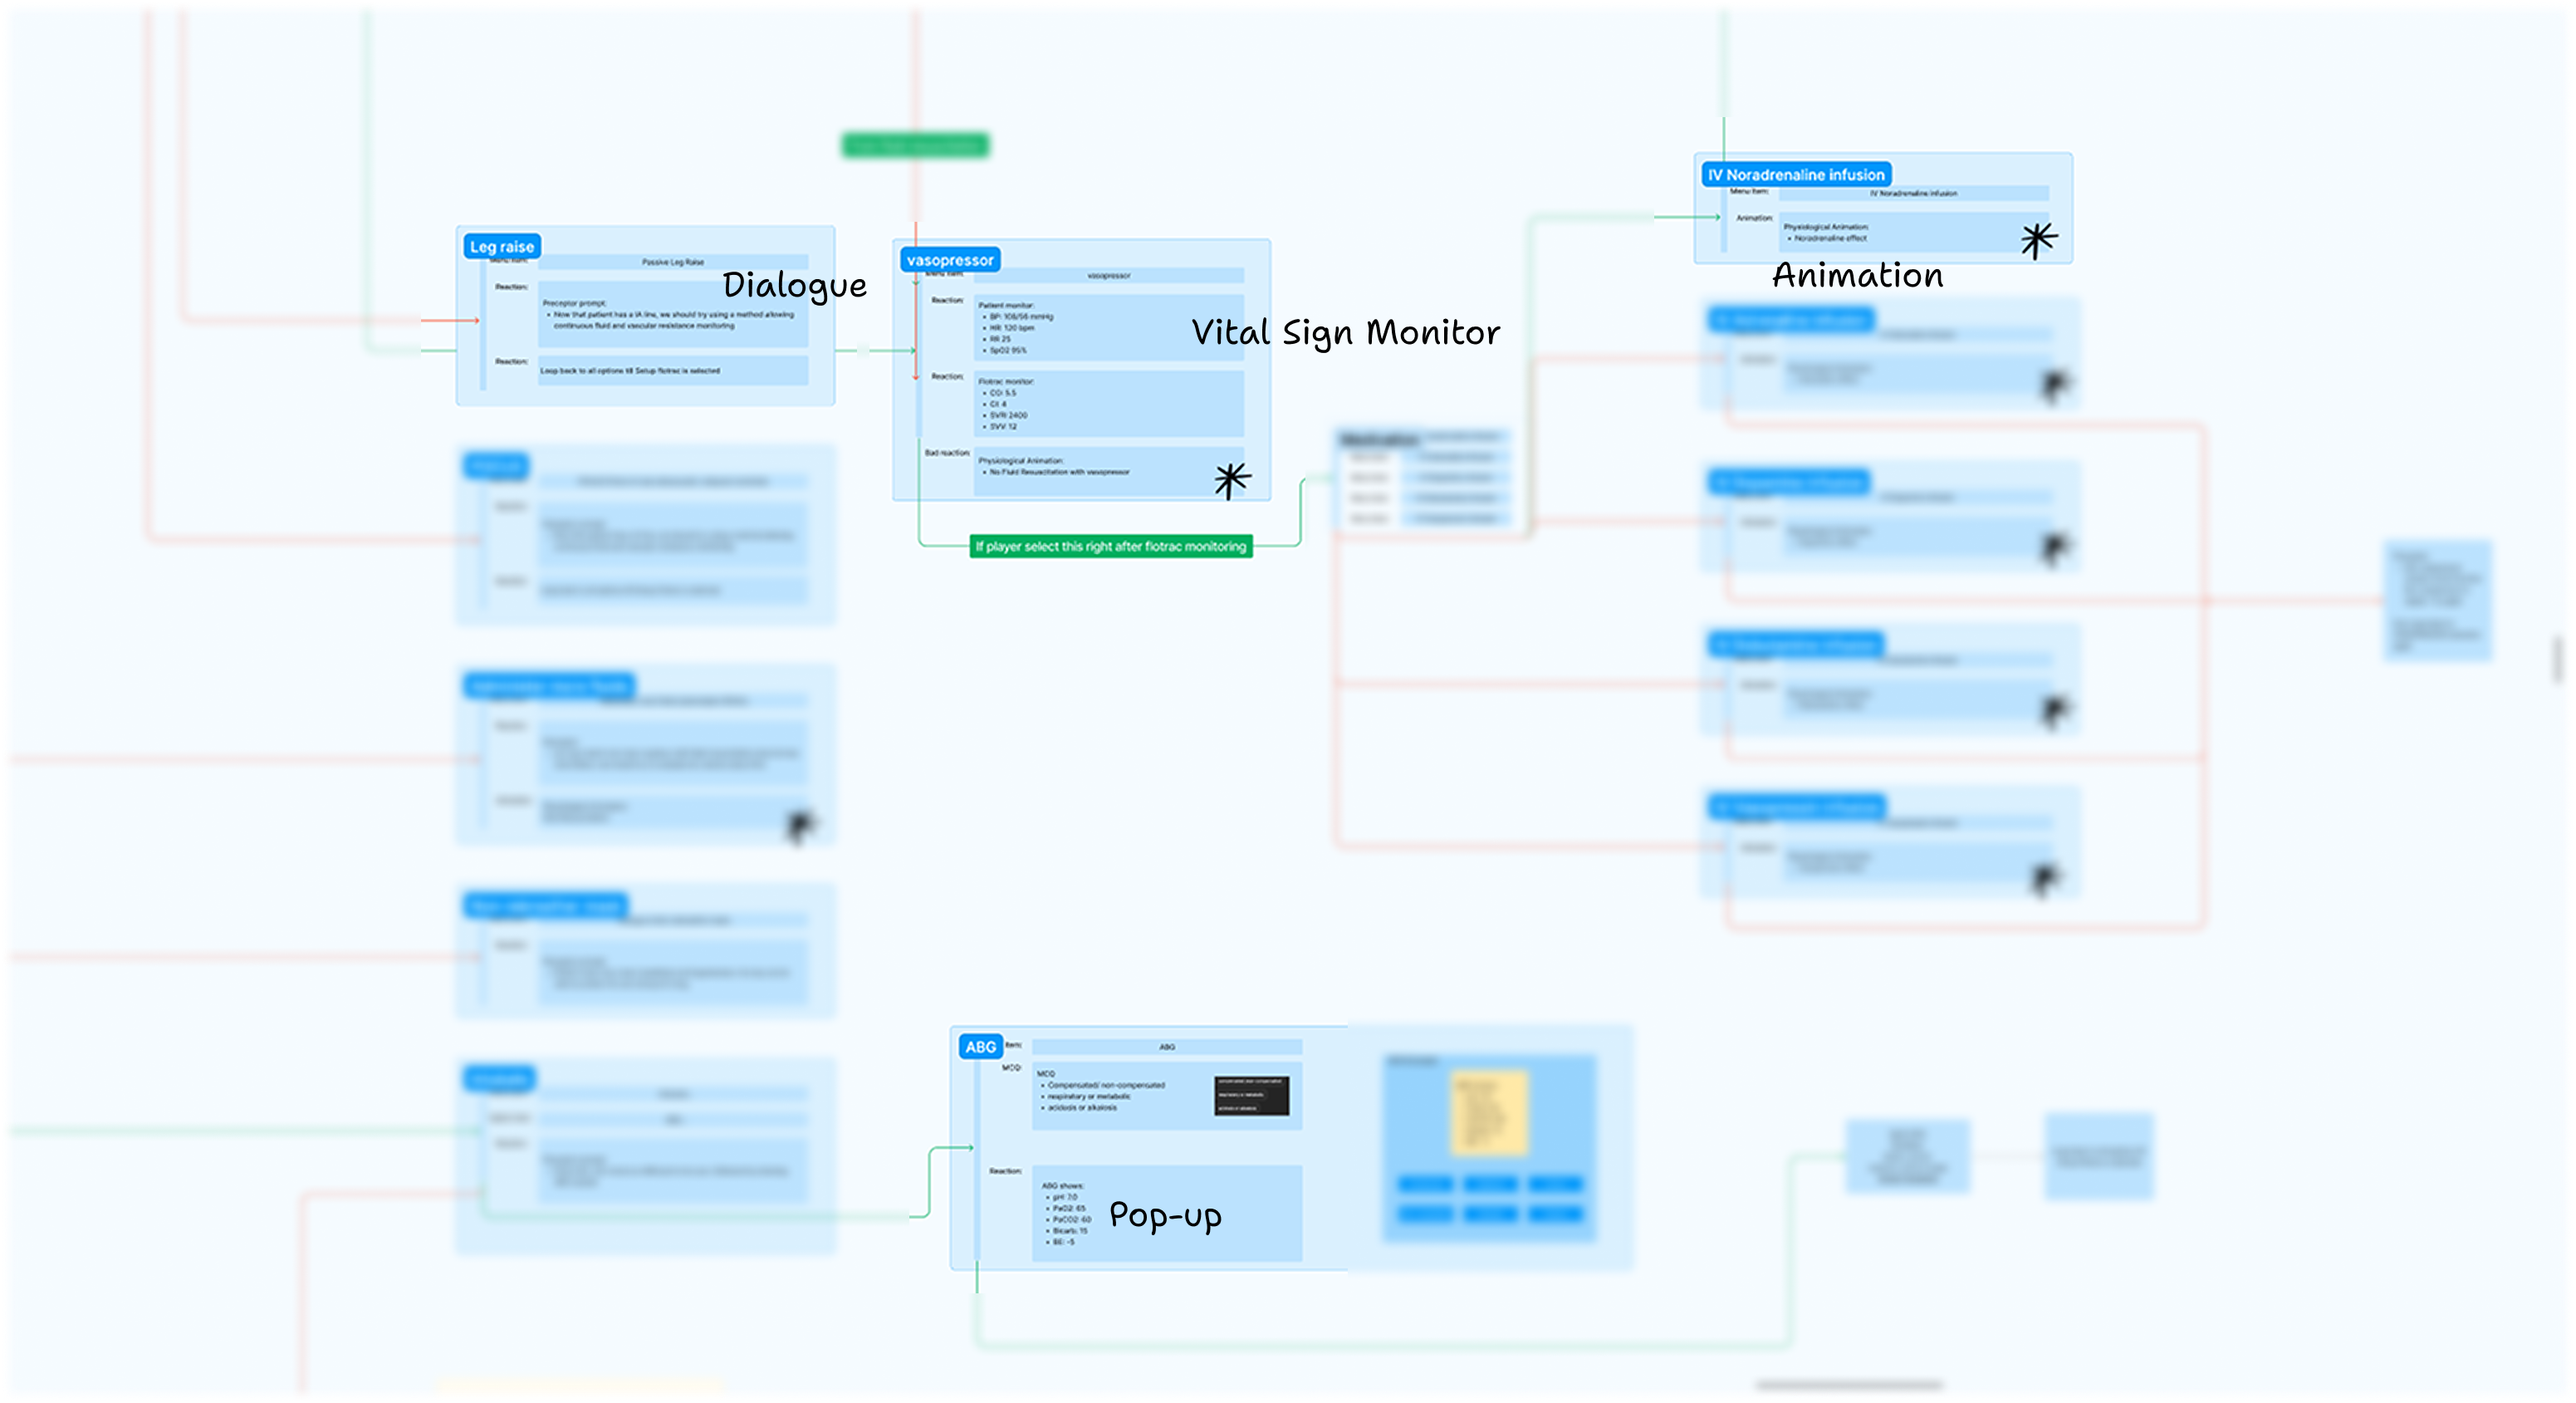
To keep clarifying scenarios like this from turning into a bottleneck, we translated each one into a consistent visual language of dialogue, vital-sign monitors, animations, and pop-ups — something both nurses and developers could read the same way.
05 / Emerging need one
Building for patients who react differently.
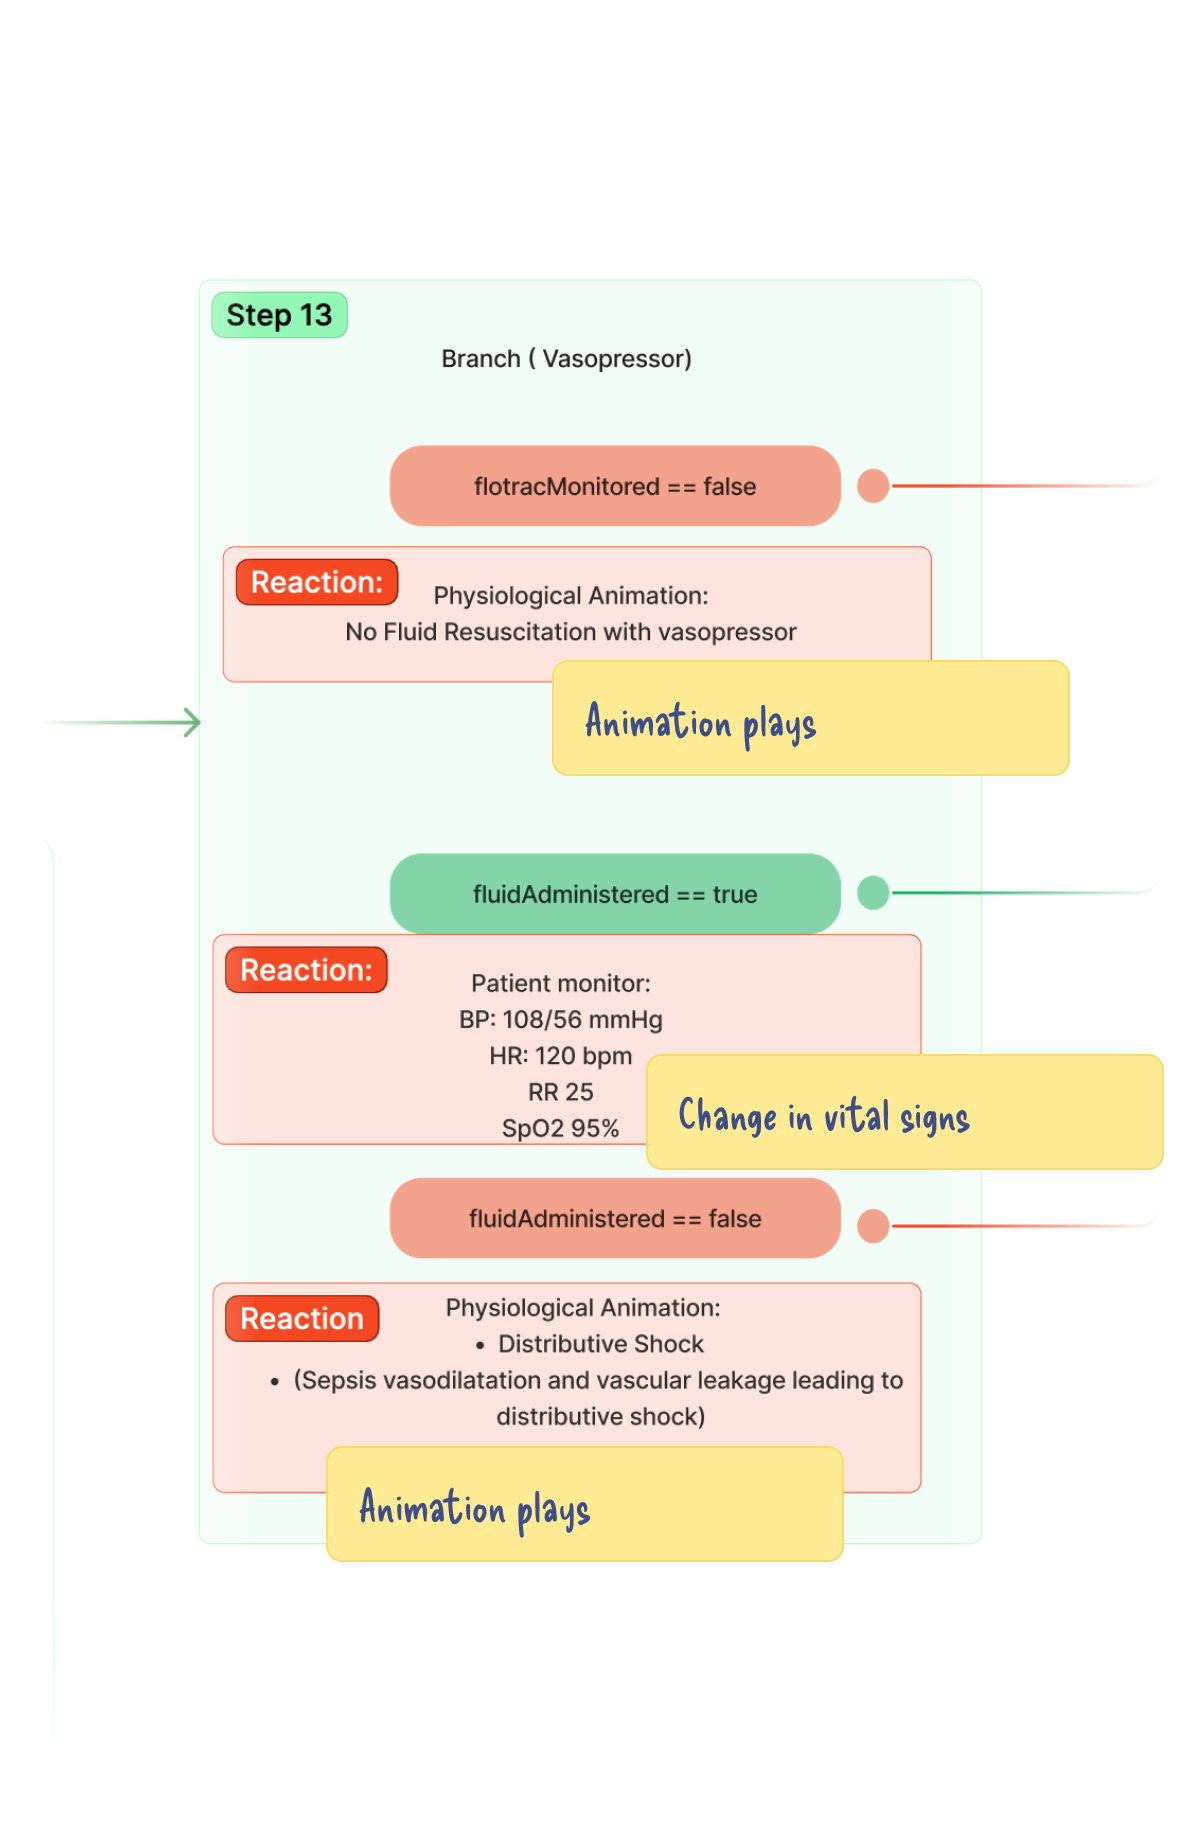
The biggest challenge was deconstructing dozens of patient scenarios and finding the patterns that could actually be programmed. I worked closely with developers to map the system's logic, leaning on my engineering background to keep every scenario realistic and scalable.
The next intervention to take depends on the patient's presentation.
A senior nurse
That single sentence, repeated by nearly every practitioner we spoke to, became the requirement behind the Modular Patient Presentation System — letting administrators simulate different equipment configurations and reactions, and assemble realistic scenarios without a developer in the loop.
06 / Emerging need two
An exhaustive list of medications was never going to be possible.
Medication is one of the most common treatments in any scenario, but it carries its own complexity — when and where to administer, dosage, delivery method, limits, increments. As we gathered detail, it became clear that no list of medications we compiled up front would ever be complete.
So instead of trying to enumerate every medication in advance, we built the Button Manager: a panel that lets senior nurses add new medication options themselves, set the correct dosage and status, and attach a reaction — all without waiting on a developer.
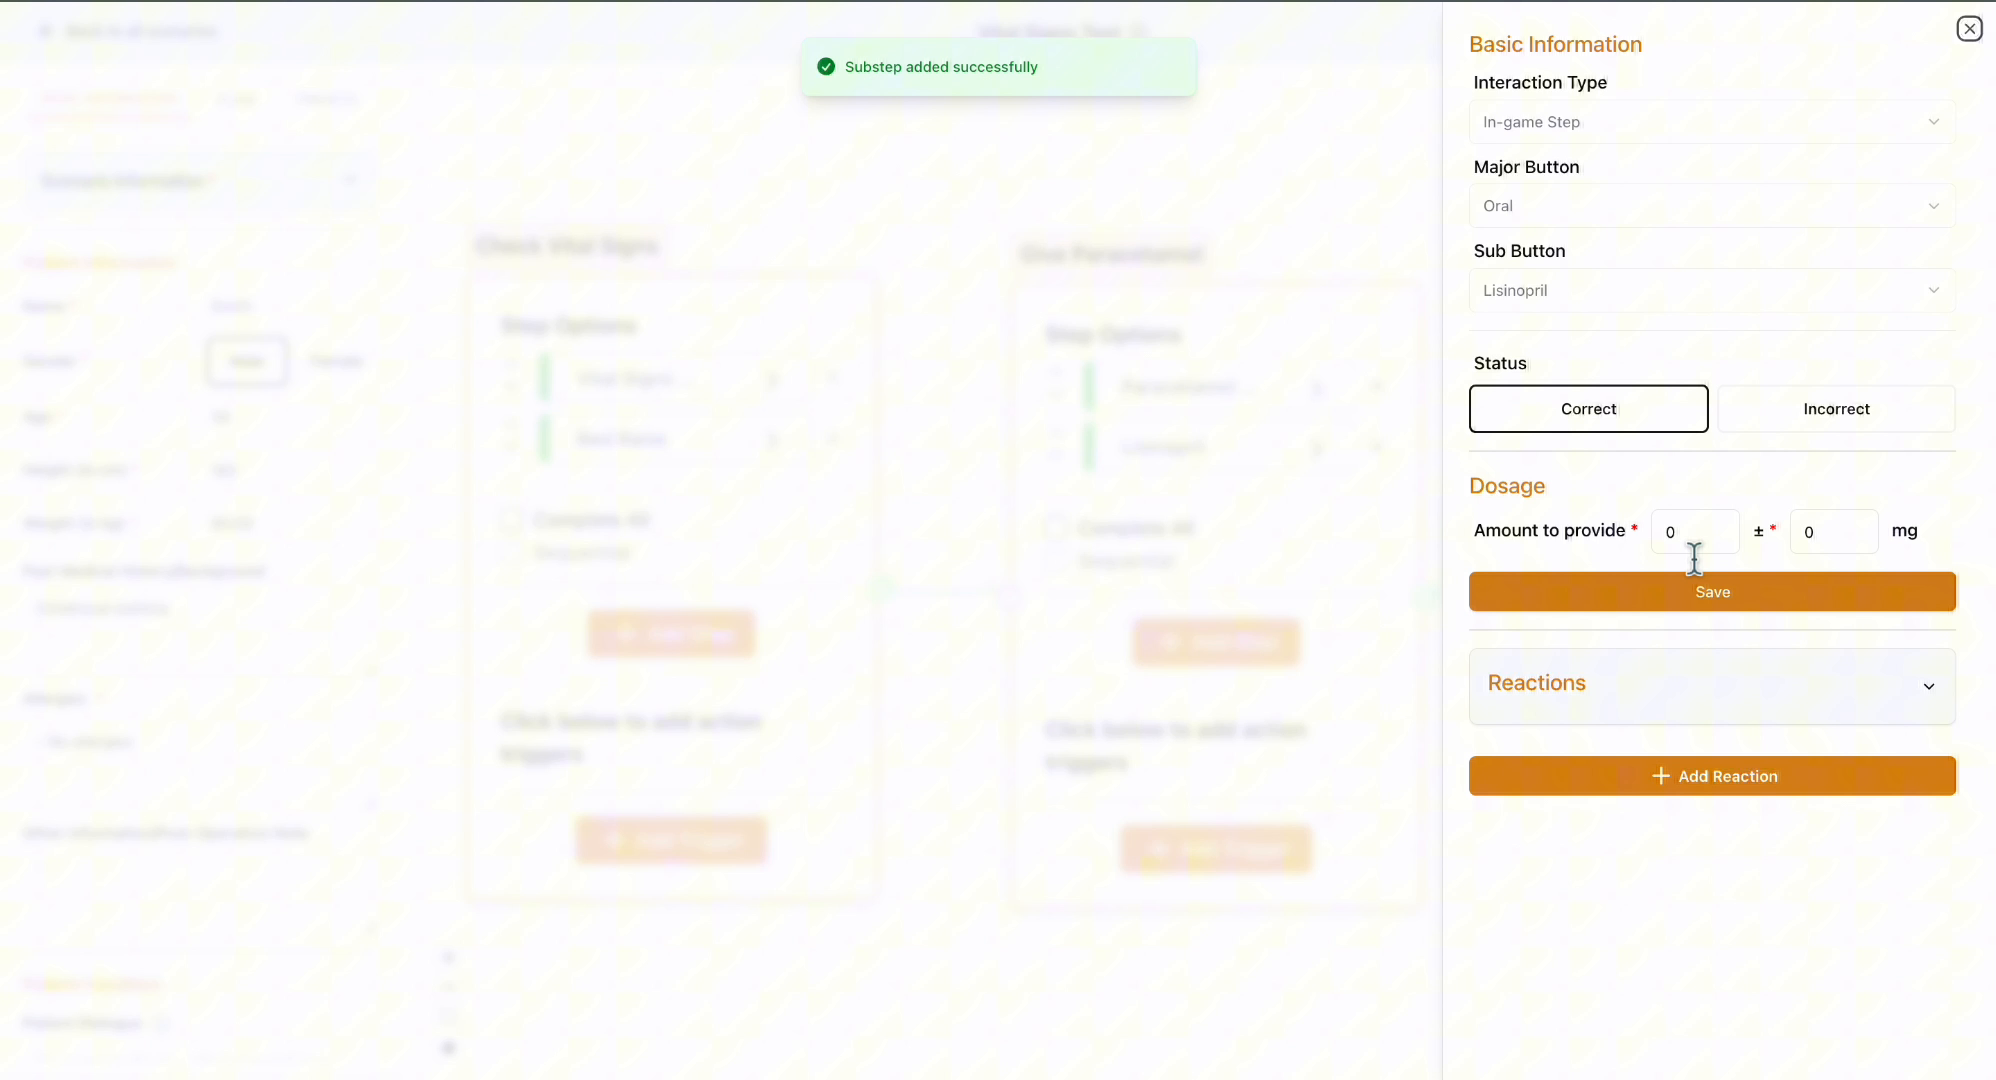
As new scenarios arrive, the medications they need are just as likely to be missing from the system as present. The Button Manager turned that gap from a recurring development request into something senior nurses could close themselves, in minutes.
07 / Reflection
Observation fosters empathy, and this was a mental gymnastics of its own.
Working on this project gave me a newfound appreciation for nurses. Most people recognise that nursing takes passion and emotional resilience — after our first ICU visit, I realised how much more is involved. Beyond emotional strength, nurses need deep medical knowledge too, something usually associated more with doctors.
This project also pushed my engineering mindset harder than most: extracting patterns from complex information, understanding intricate linkages, and building logical flows that stayed both realistic and scalable. Requirements kept emerging as we tested with the client, and gathering everything upfront was never realistic — so we designed and built in parallel with that uncertainty, rather than waiting for it to resolve.
Overall, this was a genuinely rewarding experience — one that strengthened my ability to empathise with users while sharpening how I reason through complex, ambiguous systems.